
For providers
Auth approved. Claim denied. Cash stuck in A/R.
We find where staff hours and cash stall, from scheduling to payment, then rebuild and run it as your AI operating partner.
Who it is for
Find your segment.
- Often first: A/R follow-up, benefit rechecks or the denial worklistMeasured by: Days to billable, denial aging, touches per claim
- Often first: Medicaid renewals, sliding fee or PPS and wraparound billingMeasured by: Coverage gaps, wrap reconciliation, denials
- Often first: Booking packets, implant invoices or carve-out paymentsMeasured by: Cases held before billing, carve-outs paid
- Often first: Benefit breakdowns, attachments or EOB postingMeasured by: Claims held for attachments, unposted EOBs
- Often first: Referral intake, NOA and NOE timing or unsigned ordersMeasured by: Billing holds, late notices, intake turnaround
- Often first: Authorized units or drug billingMeasured by: Units used against auth, denials by reason
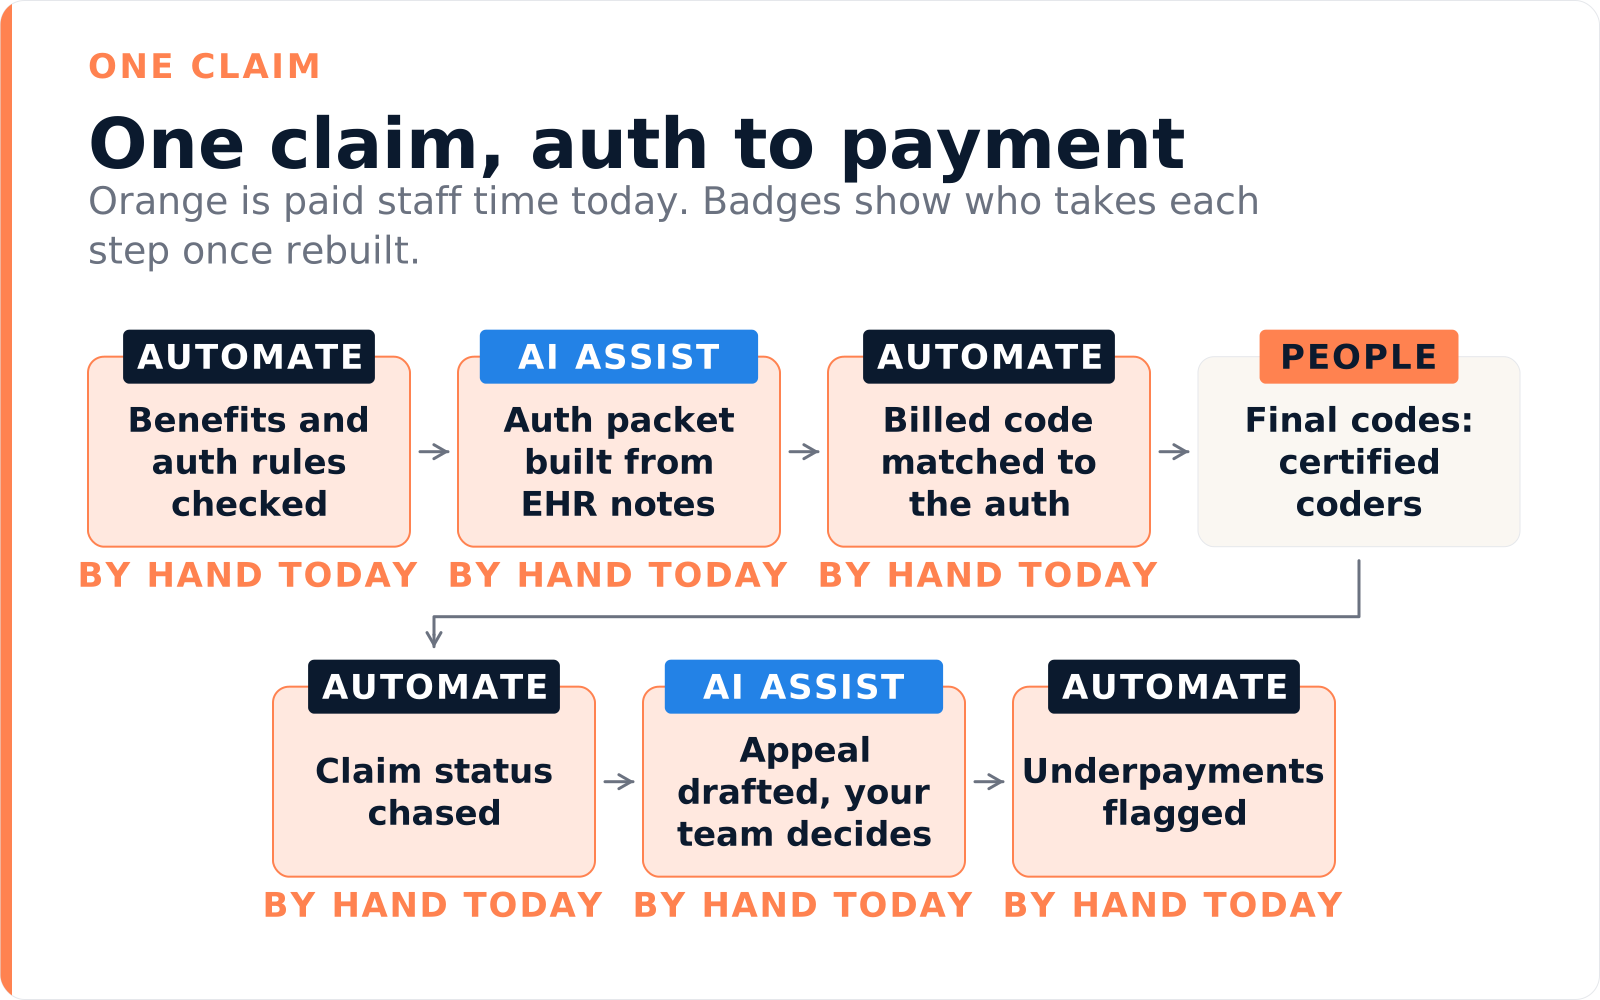
One claim, auth to payment
Who takes each step, and who approves it.
- Benefits and auth rules checked before the visitAutomation
- Auth packet built from EHR notes and submittedAI, person checks
- Billed code matched to the approved authAutomation
- Final codes selected by your certified codersYour staff decide
- Claim status chased; rejections routed to an ownerAutomation
- Denial appeal drafted; your team decides whether to send itAI, person checks
- Payment posted and underpayments flaggedAutomation
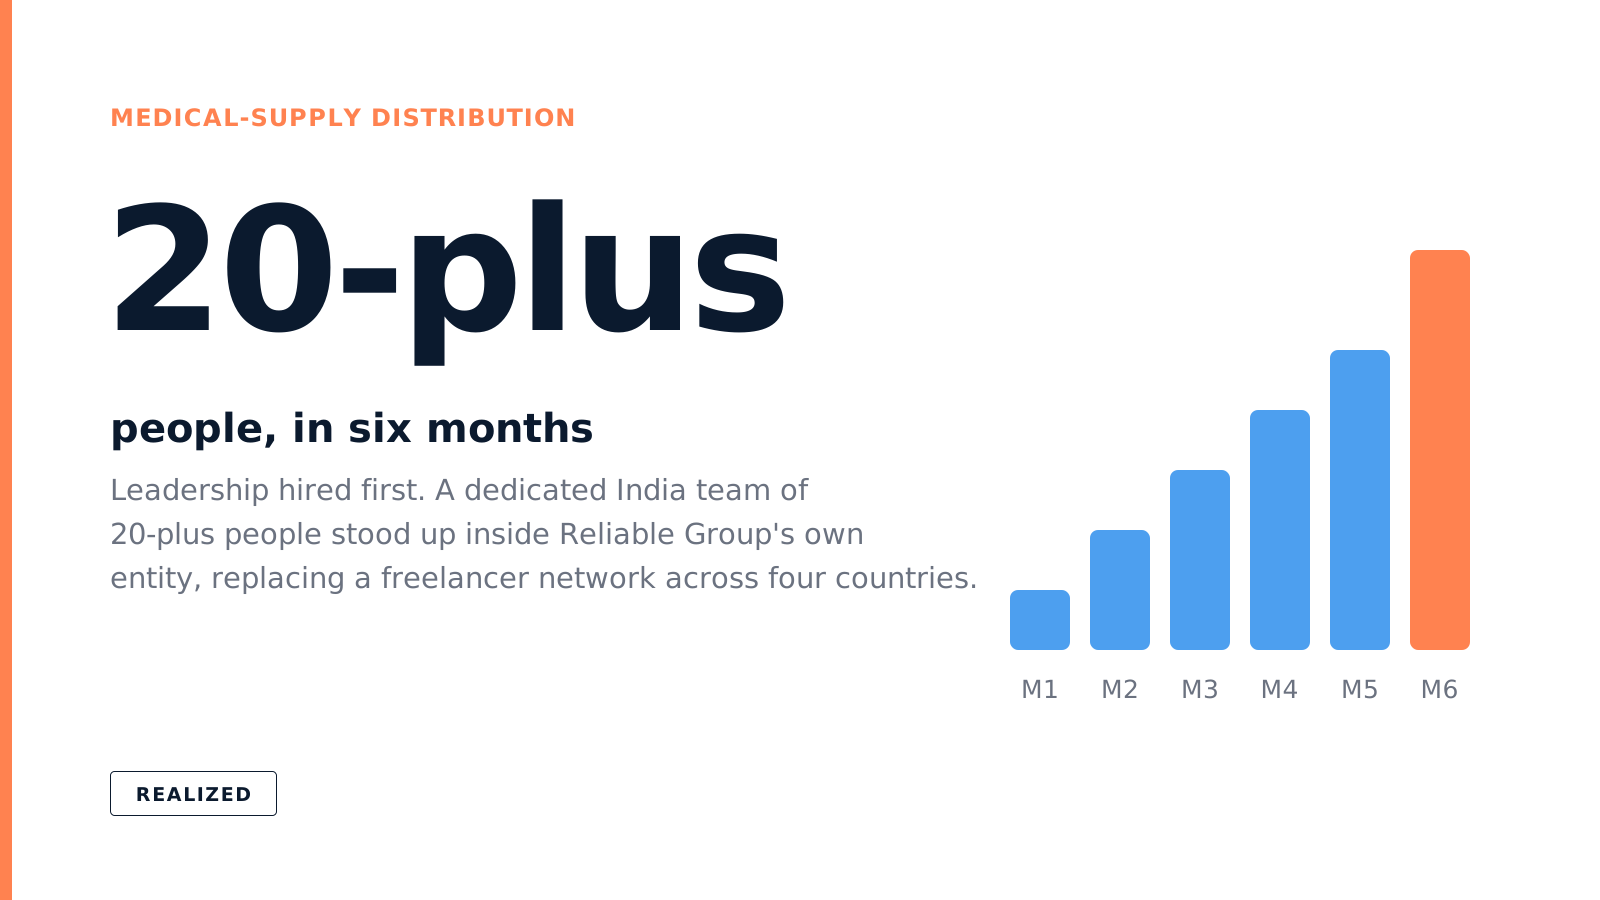
Medical-supply distribution
Healthcare servicesProKure Digital: a 20-plus person India team in six months
How we handle regulated data
Design posture, not certification
- BAA
- Where a department handles protected health information, we execute a business associate agreement before Trace is installed or any data is accessed.
- HIPAA
- We execute a Business Associate Agreement before any engagement that touches PHI, and PHI is accessed only inside client-controlled systems by named individuals. Our first healthcare engagement under BAA is in progress.
- Posture
- Ready and aligned describe design posture, not certification. Reliable Group does not currently hold SOC 2 or ISO 27001 certification; our teams operate inside client-certified environments under client controls.
- Notice
- We deploy Trace only after your organization has given team members the written notice required in your state; we provide the notice template.
Questions provider leaders ask
We measure one patient access or revenue cycle department, rebuild the queues that take the most staff hours, and run them inside your organization: rules-based automation first, AI where documents need reading, your people for judgment. It starts with a fixed-fee discovery.
Tools cover the steps they were bought for, and vendors run their own process. We measure where your staff hours still go around them, then rebuild those queues in your systems, keeping tools that work. If the map shows nothing worth rebuilding, it says so.
A fixed fee for a six to eight week discovery of one department. It ends in a workflow map and a fixed-price proposal for the first build. The build is priced separately, with no obligation to continue afterwards.
Neither. Your PM system, EHR, clearinghouse and payer portals stay as they are, under your logins and access controls. We build against what you run today, whether Epic, athenaOne, NextGen, eClinicalWorks or a mix left over from acquisitions, one department at a time.
No. Clinical documentation, medical necessity, final code selection and peer-to-peer calls stay with your clinicians and certified coders. We work the administrative queue around them: the verification queue, the avoidable denial, the stalled credentialing file.
Yes. We execute a business associate agreement before Trace is installed or any data is accessed. PHI is accessed only inside client-controlled systems by named individuals. Any team running the work is managed by us, in your entity or ours, where your payer contracts allow.
Next step
Stop guessing how your operation works.
Start with a fixed-fee discovery: one department, six to eight weeks, a workflow map and a fixed-price proposal for the first build.